
Metastatic Breast Cancer: Treatment Options, Goals Of Care, And Potential Side Effects

Metastatic breast cancer refers to disease that has spread beyond the breast and nearby lymph nodes to other organs such as bone, liver, lung, or brain. Treatment for metastatic disease typically focuses on systemic approaches that circulate through the body, and on local measures for symptom control or specific lesion management. Goals of care may include reducing tumor burden, relieving symptoms, preserving physical function, and maintaining quality of life; treatments and expected effects vary by biology of the tumor, prior therapies, and individual health status.
Therapeutic planning for metastatic breast cancer often integrates several modalities. Systemic therapies commonly used include hormonal agents for hormone receptor–positive tumors, targeted drugs that interfere with specific molecular pathways, cytotoxic chemotherapy, and, in selected cases, immunotherapy. Local treatments such as radiation or surgery can be applied to control pain, prevent complications, or manage isolated metastases. Potential side effects span from fatigue and nausea to hematologic changes and organ-specific toxicities, and they typically differ by treatment class and individual factors.
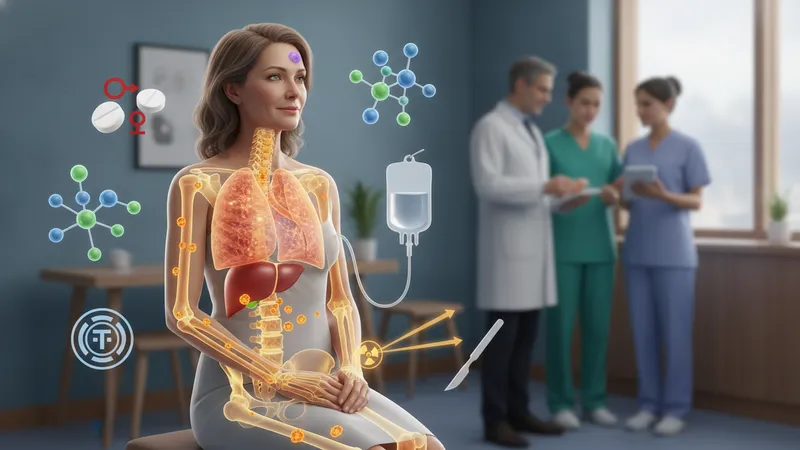
- Hormone therapy: treatments that modulate estrogen or androgen signaling for hormone receptor–positive disease, often used alone or with targeted agents.
- Targeted therapy: agents directed at molecular features such as HER2, CDK4/6, PI3K, or PARP pathways; these are selected based on tumor testing.
- Cytotoxic chemotherapy and immunotherapy: systemic cytotoxic agents are used for tumors that require more immediate control; immune checkpoint inhibitors are used in specific biomarker-defined situations.
Hormone therapy generally applies to tumors that express estrogen and/or progesterone receptors; examples of approaches include aromatase inhibition, selective estrogen receptor modulation, or estrogen receptor degradation. Targeted therapies are matched to biomarkers such as HER2 positivity, PIK3CA mutations, or BRCA alterations and may be combined with endocrine agents in some settings. Cytotoxic chemotherapy uses drugs with direct cell-killing effects and may be administered in cycles. Immunotherapy, where applicable, targets immune pathways and is typically considered when specific biomarkers or clinical contexts suggest potential benefit.
Goals of care in metastatic breast cancer are individualized and may include life-extension, symptom control, preservation of functional status, or a combination. Decisions typically weigh likely benefits against potential side effects and the patient’s preferences and life circumstances. Clinicians often discuss probable outcomes in ranges rather than absolutes and may prioritize treatments that are likely to control symptoms and maintain independence. Shared decision-making and regular reassessment are commonly used frameworks to align therapeutic choices with changing goals over time.
Potential side effects vary by treatment class. Hormone therapies often have effects such as hot flashes, joint symptoms, or metabolic changes. Targeted agents can produce class-specific toxicities like diarrhea, rash, or laboratory abnormalities. Chemotherapy frequently causes fatigue, nausea, hair loss, or low blood counts, depending on agents used. Immunotherapy can cause immune-mediated inflammation of organs. Side effects may be acute or cumulative, and their management often involves dose adjustments, supportive medications, or symptomatic treatments coordinated by the clinical team.
Monitoring response typically uses imaging studies, clinical assessment, and, in some cases, blood-based markers or molecular assays. Imaging intervals may vary with disease pace and treatment type; symptomatic changes reported by patients are also an important component. Response assessment frameworks such as RECIST are used in research and often inform clinical interpretation, but practical follow-up commonly combines objective measures with patient-reported outcomes. Regular monitoring allows timely modification of therapy when progression or intolerable toxicity occurs. The next sections examine practical components and considerations in more detail.